

Hockey Hip Assessment: Femoral Ante-/Retro-version
The underlying assumption that hockey players (and athletes in general) are structurally and neurologically symmetrical is grossly misguided. In fact, structural asymmetries in conjunction with asymmetrical movement tendencies can be an underlying factor in a lot of the dysfunction our players present with and in common hockey injuries. This is true even of traumatic injuries; when a joint is in suboptimal alignment, stability is compromised.
It's no mystery to the hockey community that hip injuries are an epidemic. CAM impingement and sports hernias have been getting a lot of press over the last 5 years and adductor ("groin") and hip flexor strains have become accepted as a necessary evil. I strongly believe that these injuries result because of a general lack of awareness of the predisposing factors that contribute to them and the necessary off-ice training strategies to prevent them. This belief isn't at all theoretical; over the last two years we have completely eliminated adductor and hip flexor strains in our hockey players through off-season training alone. In other words, we have 2.5-4 months to "injury-proof" a player at Endeavor Sports Performance during the Summer, and then the player returns to his team and we don't hear back from them until the next off-season. All of our players from last year have returned and we had ONE player sustain an injury to his hip flexors. It was a bilateral strain that resulted from an unexpected high speed collision to the back of his legs, which resulted in a rapid hip hyperextension and slight bilateral tear. It was a freak occurrence. This player will get struck by lightning on his way to cash in his winning lottery ticket before that happens again. Other than that, not a single game missed for hip-related injuries at all. The overwhelming majority of hip injuries and nagging pains are completely unnecessary.
One of the keys in preventing unnecessary hip injuries is to have an in-depth understanding of the player's anatomical/structural composition. In this regard, CAM impingement has received a lot of attention recently and rightfully so. Another frequent structural deviation that hasn't received as much attention is femoral "version". Femoral version is a measure of the angle of the femoral neck relative to a horizontal line through the two femoral condyles.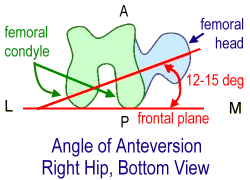
Demonstration of calculation of the angle of femoral version
While I think the above cartoon schematic is instructive for understanding how femoral version is calculated, I think this picture from Bill Hartman's post (Hip Mobility: Femoral Anteversion) better illustrates the contrast between "normal" and excessive anteversion.
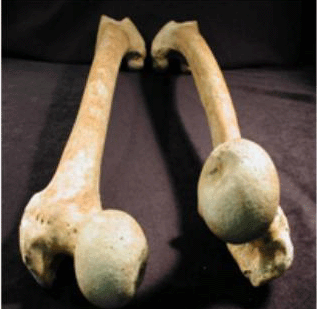
Can you imagine how the orientation of the knee, lower leg, and foot would change if the femur on the right was re-oriented so that the femoral neck was the same as the one on the left?
Excessive femoral version, in either direction, will have a significant effect on the performance of the entire body and a failure to recognize the presence of such a structural deviation may result in off-ice training exercises that appear "correct" externally to be damaging internally. As a result, it is worth the time to assess for femoral version angles in hockey players. Check out the video below for a quick walk through on how you can assess for excessive hip ante- or retro-version in just a few minutes.An idea that didn't come through sufficiently in the video is that EVERY femur has properties of ante- or retro-version. 8-15° is considered within normal limits and "excess" is generally considered anteversion > 30° and retroversion less than 5°. That said, any deviation outside of normal limits is going to have an effect on the availability of rotational movement. When I mentioned that I was thinking Matt's left femur was retroverted and the right was anteverted (outside of the normal limits in those directions specifically), I probably should have said that left femur was more retroverted than right, or that his right was more anteverted than his left. Following Craig's Test, it was apparent that his left femur was in fact "normal" (version within normal limits), but the right femur was anteverted. An important take home from this assessment is that the total rotation ROM is the true indicator of unilateral limitations. Matt had more expressed external rotation ROM on the left than right, and more internal on the right than left, but the total rotation ROM between the two sides was relatively equivocal. This indicates that differences in either internal or external rotation ROM from one side to the other are either:
- An ossessous adaptation that should be recognized and appreciated, but cannot be corrected; or
- A positional change in the pelvic structures that causes a change in the expression of rotational ROM direction tendencies
